



An LLM for healthcare is a large language model adapted to medical language, clinical workflows, and health data, used for tasks like decision support, documentation, and patient communication. In 2026, both open-source medical models and enterprise platforms package this capability for hospitals and clinics. The deciding factors for adoption are validation, privacy compliance, and governance, not raw model size. This guide covers the landscape, use cases, risks, and an implementation roadmap for healthcare organizations.
The pace of change in medical AI has been startling. In just a few years, large language models have moved from research curiosities to tools that draft discharge summaries, summarize patient histories, and support differential diagnosis. Health systems that once ran pilots in innovation labs are now deploying these systems in production, and regulators are racing to keep up.
The reason is simple economics. Clinicians spend a large share of their day on documentation and information retrieval, not patient care. Payers and providers are drowning in unstructured text: progress notes, radiology reports, discharge letters, and research literature. An LLM for healthcare attacks exactly this bottleneck, because language is both the medium of medicine and the biggest cost driver.
But adoption is not a plug-and-play exercise. Medical language is dense, errors carry clinical consequences, and privacy law constrains every data flow. This article walks through what LLMs actually do in healthcare, where they deliver value today, where the risks lie, and how a healthcare organization should approach implementation in 2026.
What Is an LLM and How It Applies to Healthcare
Definition of LLM
A large language model is a neural network trained on massive text corpora to predict the next token in a sequence. Modern LLMs are built on the transformer architecture, which uses attention mechanisms to weigh the relevance of every word in a passage against every other word, capturing long-range context that older models missed.
Training happens in two stages. Pre-training teaches the model general language and world knowledge from internet-scale text. Fine-tuning then adapts that general capability to a domain, such as instruction tuning on clinical dialogue or continued pre-training on medical literature. For healthcare, fine-tuning on curated medical corpora is what turns a general model into a medical large language model with clinically useful behavior.
Core Technologies
Three technical shifts explain why LLMs outperform the rule-based NLP systems hospitals used a decade ago. First, tokenization lets models handle the full vocabulary of medicine, including drug names, ICD codes, and abbreviations, as composable units. Second, attention mechanisms allow the model to connect a symptom mentioned on page one of a chart with a medication listed on page twenty, something keyword systems could never do reliably. Third, generative capability means the model can produce new text, a summary, a draft note, a patient-friendly explanation, rather than only classifying or extracting.
That generative shift is the double-edged sword. Extraction systems could only return what existed in the source text. An LLM can synthesize, which enables summarization and drafting but also introduces hallucination risk, a central theme in every healthcare deployment.
Current Landscape of LLMs for Healthcare
The market has split into two complementary tracks: open-source medical models that organizations can host and adapt themselves, and commercial platforms that package managed LLM services with compliance and integration built in.
Open-Source Initiatives
The open-source medical LLM movement has matured fast. Meditron, an open model fine-tuned for clinical reasoning, demonstrated that community-driven efforts could approach the performance of far larger proprietary models on medical question-answering benchmarks. MedGemma, built on Google's Gemma family, extends this to multimodal medical tasks, including radiology image understanding. Other efforts target specific niches: models fine-tuned on clinical notes, on non-English medical corpora, and on low-resource settings where commercial APIs are unaffordable.
Open-source matters for healthcare for a specific reason: data control. A hospital that self-hosts a medical LLM can keep clinical data entirely inside its own infrastructure, which simplifies HIPAA and GDPR compliance enormously. The trade-off is operational burden, because self-hosting requires ML engineering talent, GPU infrastructure, and an internal validation process that many health systems lack.
Commercial Platforms
Enterprise platforms take the opposite approach: they handle the infrastructure and compliance, and the health system focuses on workflow. Microsoft's Azure AI portfolio offers health-specific models and responsible AI tooling, with HIPAA-eligible services and integration into the Office ecosystem many clinicians already live in. AWS Bedrock provides managed access to multiple foundation models with healthcare data-use agreements. Innovaccer's Gravity platform packages LLM capabilities inside a data-activation layer that already connects to EHRs, targeting use cases like care-gap identification and population health.
The commercial pitch is speed and liability clarity. Vendors carry compliance certifications, offer uptime guarantees, and increasingly provide audit tooling. The cost is vendor lock-in, per-token pricing that scales unpredictably, and less control over model behavior when the vendor updates the underlying model.
Clinical Use Cases
Decision Support and Diagnosis
Clinical decision support is the highest-stakes and most carefully watched use case. Here, LLMs assist rather than decide: they surface relevant differential diagnoses, retrieve applicable clinical guidelines, and stratify risk from patient data.
In practice, a clinician queries the system with a patient presentation, and the model returns a ranked differential with supporting evidence pulled from the chart and from medical literature. Studies on models like GPT-4-class systems have shown strong performance on medical licensing exam-style questions, but exam performance is not bedside performance. The honest framing is that these systems function as a tireless second reader, catching considerations a fatigued clinician might miss, while the clinician retains full responsibility for the decision.
Risk stratification is a quieter but equally valuable application. An LLM that reads a full chart can flag patients whose scattered notes suggest deterioration risk, surfacing patterns no single note reveals.
Documentation and EHR Summarization
Documentation is where LLMs deliver the most immediate, measurable ROI. Ambient clinical documentation tools listen to the patient encounter and generate a draft note for clinician review, cutting documentation time dramatically. LLMs also draft discharge summaries from inpatient stays, generate patient-friendly after-visit summaries, and suggest medical coding from note content.
The key design principle is draft-and-review: the model produces, the clinician approves. This keeps the human in the loop where liability lives, and it matches how clinicians already work with templates and scribes.
Imaging and Multimodal Applications
Multimodal models combine text and image understanding, and radiology is the natural home. A multimodal LLM can draft a report from imaging findings, answer a clinician's questions about a specific study, and cross-reference the image with the patient's history. Pathology is following the same pattern, with models that describe tissue slides and flag regions of interest for the pathologist.
The critical caveat: these models assist interpretation, they do not replace the radiologist. Deployment patterns keep the image data inside the health system's network and position the model output as a preliminary read or a report draft.
Patient Engagement and Conversational Agents
Patient-facing conversational agents handle symptom triage, medication counseling, appointment preparation, and chronic disease coaching. These systems must be engineered with conservative guardrails, escalating to human care whenever symptoms suggest urgency. Done well, they extend clinical capacity between visits, especially for chronic condition management where patients need frequent, low-complexity touchpoints.
Benefits and Opportunities
Improved Access in Low-Resource Settings
The most underappreciated opportunity for LLMs in healthcare is global equity. In regions with severe clinician shortages, a well-designed LLM system can extend the reach of each available professional. Humanitarian and research projects have deployed medical LLM assistants to support community health workers with triage guidance, protocol lookup, and translation across language barriers.
Open-source models are the enabler here. A model that runs on modest hardware, fine-tuned for local languages and local disease profiles, can operate where commercial API costs and connectivity would make cloud services impractical. This is where an LLM for healthcare shifts from efficiency tool to access multiplier.
Personalization and Preventive Care
LLMs excel at synthesizing heterogeneous patient data into coherent, actionable guidance. Combined with wearable and patient-generated health data, a model can surface personalized prevention recommendations, flag deviations from a patient's baseline, and tailor communication style to health literacy levels.
Precision medicine applications go further, integrating genomic reports, family history, and literature into individualized risk discussion. The LLM acts as the translation layer between dense specialized data and a conversation the patient can actually participate in.
Research Acceleration
On the research side, LLMs compress literature review from weeks to hours, generate hypotheses by cross-linking findings across papers, and support drug discovery by analyzing compound descriptions and biomedical literature at scale. Every major pharma organization now runs internal LLM programs for exactly these tasks.
Challenges and Risks
Data Privacy and Security
Privacy is the gating constraint on every healthcare LLM deployment. HIPAA in the United States and GDPR in Europe impose strict requirements on how protected health information is processed, and feeding raw clinical text to a third-party API can constitute an impermissible disclosure.
Organizations address this through several layers: self-hosting or HIPAA-eligible services with business associate agreements, de-identification pipelines that strip identifiers before inference, and contractual guarantees that vendor-retained data is not used for model training. De-identification itself is subtle, because clinical text contains dates, rare conditions, and contextual details that re-identify patients even after obvious identifiers are removed. LLM-based de-identification tools now help here, an LLM protecting data for other LLMs.
Bias, Fairness, and Equity
Medical LLMs inherit the biases of their training data. If the literature underrepresents certain populations, or clinical notes encode historical disparities in care, the model reproduces those patterns in its outputs. Documented failure modes include differential diagnostic accuracy across demographic groups and patient-facing communication that assumes higher health literacy than many patients have.
Mitigation is a process, not a checkbox: evaluate performance stratified by demographic group, use diverse fine-tuning data, involve clinicians from the served populations in validation, and monitor deployed systems for drift in subgroup performance. Fairness monitoring belongs in the same dashboard as accuracy monitoring.
Regulatory and Validation Hurdles
Regulatory posture depends on the claim being made. An LLM that summarizes notes is a productivity tool; an LLM whose output influences diagnosis or treatment decisions may qualify as a medical device, triggering FDA or EMA pathways with clinical validation requirements.
The practical roadmap most organizations follow: define the intended use precisely, run retrospective validation on local data before deployment, conduct prospective silent-mode evaluation where the model runs alongside clinicians without affecting care, and maintain post-market monitoring with defined rollback triggers. Regulators in 2026 have issued adaptive frameworks for AI-enabled devices, but the burden of demonstrating safety still sits with the deploying organization.
Implementation Guide for Healthcare Organizations
Assessing Needs and Selecting a Model
Start with the use case, not the model. A documentation assistant, a patient-facing agent, and a research copilot have different requirements for accuracy, latency, and privacy. Build a selection checklist that covers: the clinical workflow being targeted, tolerance for error in that workflow, data sensitivity, budget for both inference and validation, whether open-weight self-hosting or managed platforms fit your engineering capacity, and the model size you can realistically serve and evaluate. Smaller, fine-tuned models frequently beat giant general models on narrow clinical tasks at a fraction of the cost.
Integration with Existing Systems
Integration is where LLM projects live or die. Healthcare data flows through established standards: HL7 for messaging, FHIR for API-based data exchange, DICOM for imaging. A production LLM system connects to the EHR through FHIR interfaces to pull patient context, and to PACS for imaging studies, then returns outputs into the clinician's existing workflow rather than a separate portal.
The architecture principle: the LLM sits behind an integration layer that handles authentication, data minimization, and output routing. Clinicians should never interact with a raw model endpoint; they interact with their EHR, and the LLM is invisible infrastructure.
Governance, Monitoring, and Continuous Learning
Governance turns a promising pilot into a safe production system. Core practices include model versioning with documented change logs, audit trails that record every inference and the data it touched, performance dashboards tracking accuracy and subgroup fairness, incident reporting channels for clinicians, and a defined process for updating models without silently changing clinical behavior.
The end-to-end pipeline that a governed deployment follows looks like this:
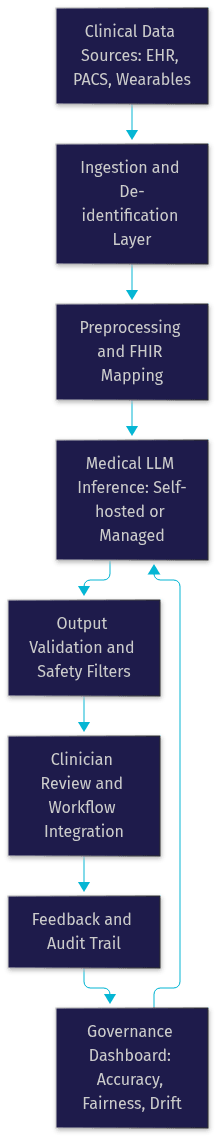
The feedback loop at the bottom is what separates a governed system from a demo. Clinician corrections flow back into evaluation sets, drift triggers retraining reviews, and the audit trail makes every output explainable after the fact.
Future Trends
Multimodal Generative AI
The near future is the convergence of text, imaging, and physiological signal models into a single holistic view of the patient record. A clinician will ask one system a question that spans the radiology report, the ECG waveform, the genomics panel, and three years of progress notes, and receive a coherent synthesis. The technical pieces exist in 2026; the integration and validation work is what remains.
Real-time Clinical Assistants
The next frontier is the bedside copilot: an assistant that responds in real time during the encounter itself, surfacing relevant history and guideline checks as the conversation happens. These systems operate under strict latency and safety constraints, because a suggestion that arrives after the decision is worthless and one that arrives wrong is dangerous. Expect early deployments to be narrow, heavily monitored, and explicitly scoped to information retrieval rather than decision-making.
Definitions Glossary
LLM for healthcare: A large language model fine-tuned or configured for medical language and clinical workflows, used for tasks like documentation, decision support, and patient communication.
Clinical decision support: Software that provides clinicians with evidence-based guidance at the point of care; LLM-based systems extend this with generative synthesis of patient data and guidelines.
FHIR (Fast Healthcare Interoperability Resources): The API-based standard for exchanging healthcare data, commonly used to connect LLM systems to electronic health records.
De-identification: The process of removing or masking patient identifiers from clinical data before it is processed by a model, a core requirement for HIPAA and GDPR compliance.
Hallucination: The generation of fluent but factually incorrect content by a language model, the primary safety concern in clinical deployments and the reason draft-and-review workflows are standard.
Ambient clinical documentation: A deployment pattern where an LLM listens to the clinical encounter and drafts the note for clinician review, reducing documentation burden.
Key Takeaways
- An LLM for healthcare delivers the most proven value today in clinical documentation, EHR summarization, and information retrieval, with decision support advancing under strict human-in-the-loop design.
- Open-source medical models like Meditron and MedGemma enable self-hosted deployments with full data control, while commercial platforms like Azure AI, AWS Bedrock, and Innovaccer Gravity offer speed and compliance packaging.
- Privacy, bias, and regulatory validation are gating constraints, not afterthoughts; HIPAA and GDPR compliance, subgroup fairness monitoring, and clinical validation determine whether a deployment survives.
- The winning architecture keeps the LLM behind an integration layer using FHIR and HL7 standards, with clinicians working in their existing EHR rather than a separate AI tool.
- Multimodal patient records and real-time bedside assistants are the 2026 frontier, but both depend on governance, audit trails, and feedback loops being in place first.
Conclusion
The LLM for healthcare transformation is real, but it is a marathon of validation and governance rather than a sprint of model releases. Organizations that succeed start with narrow, high-ROI use cases like documentation, keep clinicians in the loop on every output, and build the audit and fairness infrastructure before scaling. The technology is ready for careful adoption; the differentiator is operational discipline. If you are building healthcare applications with real-time communication needs, such as telemedicine or AI-assisted patient engagement, explore VideoSDK's documentation and the AI agents guide to see how voice and video infrastructure supports clinical workflows. What healthcare AI use case are you working on? Drop a comment, I would love to hear what you are building.
Free $20 Balance for AI Voice Agents & Video Calls
FAQ